Pain is both a symptom and a tension multiplier. In the area, the distinction between a calmness, lucid client and a degrading one can be as simple as prompt analgesia and proficient reassessment. The PUAEME008 Offer pain monitoring device rests specifically because room. It certifies that you can examine, treat, keep an eye on, and turn over an individual experiencing acute pain, within the borders of your role and regional methods. If you operate in emergency action, remote medical care, sport coverage, occasion medical, or area first reaction, this brief course can be the bridge in between basic first aid and secure, organized discomfort care.
I have instructed and analyzed variations of this unit across rescue auxiliaries, industrial emergency feedback groups, and professional support duties. The students that get one of the most out of it already have great scene skills and want even more confidence with analgesic agents, paperwork, and decision-making under pressure. This failure walks through what PUAEME008 covers, exactly how it runs in practice, the usual risks I see during analyses, and just how various occupations can use it, from nurses and physiotherapists to rescue technologies and remote medics.
What the device really covers
PUAEME008 Supply discomfort administration is a country wide acknowledged unit in Australia concentrated on acute pain assessment and monitoring in prehospital and out-of-hospital settings. It leans on three columns: systematic evaluation, evidence-based intervention within extent, and continuous monitoring with to handover. Unlike a broad discomfort management program that dives deep right into chronic problems, this system addresses the initial hours of care, where decisions are made under time stress and with minimal resources.
At a minimum, the efficiency tasks consist of examining pain utilizing verified devices, choosing a proper intervention, carrying out analgesia or using options as permitted by organisational policy, keeping an eye on for effectiveness and unfavorable effects, and documenting and interacting the therapy and trajectory. The unit recognises that technique settings vary. A country initial -responder may bring methoxyflurane and oral analgesics. An event paramedic can include intranasal fentanyl under a scientific governance version. The unit framework permits those variations as long as the prospect demonstrates safe, organised care.
Who advantages, realistically
You do not need a paramedic degree to obtain worth from this program. You do need a standard of emergency treatment or emergency treatment experience. Individuals that usually enlist include trainees upgrading from progressed first aid, mine website medics that desire structured analgesia credentials for website procedures, lifesavers and ski patrol that run under standing orders, and allied health specialists who operate at occasions or remote centers and need emergency pain monitoring abilities to fill up the void in between injury and definitive care.
For those scanning for specific paths, the unit underpins several pain monitoring training courses frequently bundled into broader skill sets. It can serve as a tipping stone into a certification program in pain monitoring for greater extents, or as a distinct credential inside emergency situation discomfort administration elective streams. For clinicians in controlled careers, it matches, instead of replaces, your specialist authorisations. Nurses, as an example, still job under their Registered nurse Expert or clinical standing orders. Physio therapists broaden their emergency toolkit for sideline or remote method but need to maintain within their local policies. Treat the device as official verification that you can provide safe, standard to intermediate analgesia within an administration framework.
The composition of a brief course
Most service providers supply PUAEME008 over a small timetable: pre-course reading and quizzes, eventually of face-to-face workshops, and scenario-based evaluation. Some suppliers stretch it to two days if they include more pharmacology and simulation. Whichever layout you choose, the flow is consistent. You start with evaluation, move to treatment, then to surveillance and handover. That rhythm repeats throughout different individual presentations: separated limb injury, stomach pain, burns, back pain after manual handling, and combined trauma.
Expect to experiment pain scales fit to different patients. Adults with clear cognition can use a numeric ranking scale, zero to ten. Children or non-verbal patients may require a faces scale or observational tools like FLACC. The trainers need to urge you secure the range with a descriptor. A five means modest pain that sidetracks yet permits discussion; an eight is severe sufficient that the individual can not locate a comfy setting. Anchoring avoids the common problem where every pain amazingly becomes a seven.
On the pharmacology side, the typical suspects show up: paracetamol, ibuprofen, methoxyflurane, and, if your carrier has the authorisation framework, intranasal fentanyl. Each agent brings an account that you must understand well sufficient to act rapidly. Methoxyflurane is effective for short, extreme discomfort, has a quick beginning, and calls for careful mentoring on self-administration. Intranasal fentanyl provides predictable analgesia when IV gain access to is not available, yet demands extensive monitoring for respiratory system anxiety. Dental agents take longer to work yet underpin secure, continual relief. I have shed matter of the moments early oral application implied that by the time we reached the ED, the client's pain was controlled without requiring escalation.
Skill components that matter on shift
Beyond reading and memorizing recall, the course develops into muscular tissue memory. There are five abilities that I push right into every friend since they hold up in genuine cases.
- Calibrated communication: ask the appropriate questions at the right time, and duplicate them after each treatment. "You claimed the pain was eight; after two mins of methoxyflurane, where is it now?" This tight loophole aids capture negative impacts early. Airway alertness: even when you give representatives with a broad safety margin, assume you can tip the equilibrium. Screen price, rhythm, effort, SpO2 if offered, and responsiveness. Document the numbers, not just your impression. Dose technique: regard organisational procedures. If the standing order claims 200 mcg intranasal fentanyl initially, confirm patient age and weight cutoffs, look for contraindications, and track collective dosing against optimums. Out in the area, disturbance results in securing mistakes; a pocket graph or psychological mnemonic saves you. Route usefulness: take into consideration the setting. In winter, intranasal absorption can be slow-moving, and nasal blockage blunts impact. In great smoky settings, methoxyflurane coaching obtains lost. Pick what will certainly function here and now, not what worked last week. Handover quality: utilize a structured style. I favor IMIST-AMBO or a comparable approach. State standard pain, intervention times and dosages, current discomfort score, negative effects, and any type of red flags you kept in mind. One minute of crisp handover conserves 5 mins of ED investigator work.
Evidence and boundaries
A short training course can not resolve the whole discomfort landscape, yet it should secure you to defensible practice. Evidence sustains multimodal analgesia: integrating acetaminophen with an NSAID uses additive advantage and lowers the demand for opioids. In the prehospital setting, breathed in methoxyflurane and intranasal fentanyl both decrease pain score by significant margins within minutes. The option hinges on availability, patient factors, and service provider training.
Boundaries matter. Persistent pain worsenings are difficult. The individual may already be on opioids, and tolerance can make first-line doses really feel inadequate. The factor is not to chase a zero. Bring the pain right into a tolerable range, mitigate distress, and stop harm. For stomach pain of unidentified cause, avoid NSAIDs if there is any hint of hemorrhaging threat, anticoagulant usage, or renal concession. For head injury and altered mentation, stay with the best agents and lower sedation capacity, and reassess non-stop. For burns and inhalational injury risk, favor agents that enable you to keep an eye on respiratory tract without confusion, and coordinate very early transport.
Assessment pitfalls I see once more and again
Cognitive overload makes clever people avoid actions. One of the most typical mistakes throughout evaluation days flow from that fact, not from lack of expertise. Candidates hurry right into treatment without a baseline discomfort score. They select a medicine and only afterwards check for contraindications. They offer methoxyflurane, after that disregard hydration advice and the maximum dose daily. They carry out intranasal fentanyl without examining the gadget seal or priming, which leads to inconsistent spray volume.
Another category is documents drift. Times obtain rounded, dosages go undocumented, and the pain rating after therapy gets replaced by unclear language like "enhanced." In genuine method, that welcomes risk. If the client deteriorates or reports negative effects, your protection is a clear record of doses, times, results, and vitals over time. If you do not like documents, turn it right into information collection. Numbers inform the story, and they sustain scientific thinking. When a client's pain drops from eight to four after initial application and after that plateaus, you have premises for a careful top-up or a plan to keep with oral agents while preparing transport.
How carriers commonly structure learning
Good pain monitoring training programs keep talks lean and press practice. Expect brief components on physiology, pharmacology, and plan, after that a great deal of time on situation job. You may rotate with stations: one focused on pediatric discomfort evaluation with developmental cues, an additional on intranasal distribution strategies with different atomisers, and a third on circumstance handover with interruptions that mimic a hectic ED. Some carriers make use of simulation labs with manikins and essential sign screens, however the majority of will certainly deal with proctors and actors. What matters is rep up until your talk track, hands, and decision-making line up without friction.
The finest programs put you on the clock. They press situations to show rapid assessment and prioritisation. That pressure, incorporated with practical curveballs, develops habits you can rely on. The facilitator needs to additionally debrief candidly. If your dosage math was shaky, they ought to stop the circumstance, set up the computation again, and view you do it without cues. Self-confidence originates from eliminating those wobble points currently, not uncovering them at 3 in the early morning on a damp roadside.
Choosing a provider that fits your world
Not all short training courses in pain management are equivalent. Search for three things. First, alignment with your local procedures and medications. There is no feeling exercising intranasal fentanyl if your solution can not authorise it. Second, trainer deepness. Ask that teaches, exactly how typically they exercise in the area, and exactly how they handle evaluation failures. Third, post-course support. A quick reference card, upgraded pharmacology sheet, and a route for refresher course training make a genuine difference 6 months later when the great information fade.
If you require a discomfort monitoring certification for work, validate that the company problems a statement of achievement for PUAEME008 and that your company acknowledges it. Some functions prefer a discomfort administration certification course that bundles this system with sophisticated resuscitation or oxygen treatment. If you are coming from nursing or physical rehabilitation, inspect whether the company tailors situation work to your setups. Sports sideline injuries ask for various muscular tissue memory than industrial crush injuries.
Specific notes for registered nurses and physiotherapists
Pain management programs for nurses and pain management courses for physiotherapists frequently share web content with PUAEME008, but your technique designs differ. Registered nurses typically run within a durable medication governance structure. If you currently provide paracetamol and advil on a ward, the novelty below is not the medicine, yet the setting and urgency. You will practice quick evaluation, stringent monitoring after intranasal opioids, and handover from prehospital settings where diagnostics are restricted. Pay extra attention to your service's standing orders for emergency discomfort management and how they mesh with the unit's skill set. For rural and remote registered nurses, this system is particularly helpful due to the fact that it matches your extended practice and aids standardise assessment across personnel with wide experience ranges.
Physiotherapists in occasion or remote job face a different problem. You see acute musculoskeletal injuries more than mixed medical instances, however you still need clear analgesia paths for cracks, misplacements, burns from tools, or spinal red flags. An offer pain administration course that includes joint relocation discomfort strategies, splinting methods that reduce discomfort without deep sedation, and risk-free methoxyflurane use fits well. You will certainly additionally discover practical suggestions on individual education: just how to urge paced breathing and positioning that lowers convulsion while you prepare analgesia, and exactly how to document pain trajectories to sustain reference decisions.
When much less is more
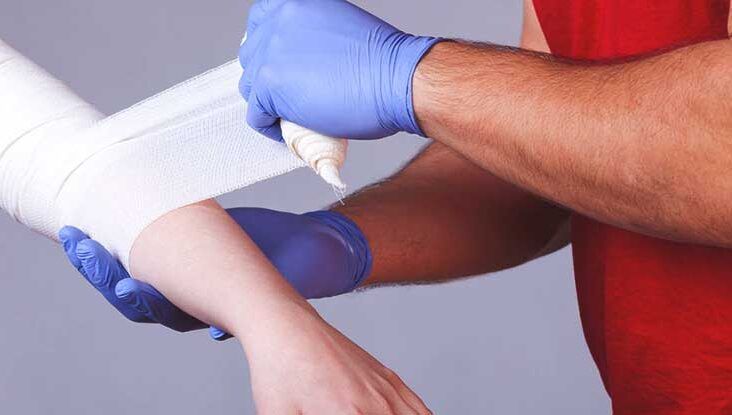
The best analgesic in some cases is not a drug. Splinting a broken wrist correctly can drop pain scores by half prior to the initial inhalation. Elevation, ice bags with a barrier, and gentle immobilisation all issue. Mentoring slow-moving, diaphragmatic breathing sounds simple up until you view a patient's pulse work out and their face unclench. In one mine website situation, an employee with a smashed finger went from nine out of ten pain to five after an appropriate splint and cold therapy, then to 3 after methoxyflurane and paracetamol. We used no opioid because the trajectory informed us we were winning without it. That judgment phone call came from cautious reassessment, not from a response to escalate.
Adverse effects and just how to remain in advance of them
Analgesics have characters. Methoxyflurane can cause lightheadedness and queasiness. Dosage within limits, ensure the client is seated, and caution them regarding the feeling prior to they breathe in. Breaks between inhalations help control adverse effects while maintaining result. Intranasal fentanyl works fast pain management certificate and naturally yet watch for respiratory anxiety, especially in older people, those with comorbidities, or any person with concurrent CNS downers on board. Keep airway adjuncts, oxygen, and a strategy all set. Oral NSAIDs are reputable yet can worsen stomach issues and connect with anticoagulants. Quick evaluating inquiries about abscess, kidney illness, and blood slimmers take less than a minute and save hours of difficulty later.
Your monitoring should mirror the danger. After intranasal opioid, check respiratory system rate, SpO2, degree of consciousness, and pain score every few minutes in the beginning, after that at longer periods if short pain management certificate courses stable. After methoxyflurane, observe for postural instability and nausea or vomiting, and maintain dose total amounts within daily restrictions based on your protocol. For oral agents, the top priority is not prompt negative effects yet intending the timing so you do not pile anesthetics carelessly. Draw up the following four to six hours and communicate the plan to the patient and getting team.
Documentation that wins regard at handover
Handover lives or dies on framework. Exercise an IMIST-AMBO style, and self-control your language to be short and certain. Begin with recognizing information and the device. State baseline discomfort and the initial important set. Listing medicines with precise doses and times. Offer the trajectory in one sentence: "Discomfort went down from 8 to 4 within 5 minutes of breathed in methoxyflurane; no negative effects kept in mind; breathing price 14 to 16 the entire time." Do with any type of ongoing danger, like presumed compartment disorder, anticoagulant use, or restricted social assistance. The emergency department does not need a novella. They require credible numbers and a tidy timeline.
The partner of documents is lawful and statistical. Solutions track analgesia use, discomfort end results, and unfavorable events to improve methods. Your accurate entrances assist enhance system performance. If your solution shifts from methoxyflurane to intranasal fentanyl based on information, your notes add to that decision. If a regulator audits an unfavorable event, accurate records secure both you and the service.
Refreshers and keeping the edge
Skills degeneration. If you do not provide analgesia consistently, your recall of dose ranges and contraindications obscures within months. Choose discomfort monitoring training programs that use refresher courses, scenario evenings, or access to on the internet microlearning. Maintain an in your area approved fast recommendation card on your set. Update it when protocols change. For individual method, construct psychological associates: on a regular sprain instance, run through in your head what you would do if the pain rose, exactly how you would certainly choose the agent, and what surveillance cadence you would certainly take on. When a genuine high discomfort instance appears, you will really feel as though you have currently been there.
Where this fits in a wider learning pathway
PUAEME008 is one system, not a location. Numerous -responders include advanced resuscitation, oxygen therapy, and injury management to stretch their ability. Some services package a pain management certificate program that blends concept, PUAEME008 Supply pain monitoring, and organisation-specific authorisations. For those looking for a pain administration accreditation for wider practice, check whether your industry requires added administration, like a professional practice standard sign-off or mentorship hours. If you are constructing a personal educational program, believe in layers: foundational emergency treatment, discomfort administration, progressed life assistance, after that unique subjects pertinent to your environment, such as burns, pediatrics, or remote logistics.
Real-world situation patterns you will certainly see in training
Good courses avoid cherry-picked easy victories. Expect intricacy. A building employee with a tibial fracture, hypotension borderline low from warm, and a language barrier. A youngster with a forearm fracture that rejects to breathe in through the mouth piece unless you transform it right into a video game. An older adult with renal disability and extreme flank pain where NSAIDs are off the table. A footballer with a disjointed shoulder that wants immediate relocation on the sideline, and a coach pressing you for speed. In each, the right action looks various. Your work is to protect the person and your permit, connect clearly, and select the least risky reliable path.
One instance from a wintertime event attracts attention. A snowboarder offered with obvious ankle deformity, discomfort nine of 10, and shuddering that covered up a climbing respiratory system rate. The group moved right to methoxyflurane, but the mask seal was bad in the wind and the individual coughed on the first breathing. We moved behind a windbreak, warmed their hands, re-coached the breathing, and secured a vacuum splint. Pain fell to 5 quickly. The group offered advil and paracetamol for sustained effect, kept track of for dizziness, and prepared transportation. No heroics, just functional changes that matched the environment.

Cost, time, and what to anticipate after you pass
Prices vary by carrier and area, however a single-unit short training course normally rests within a moderate expert growth budget plan. Expect a day inactive, perhaps two if you select an increased program. After successful assessment, you must get a declaration of attainment. Maintain it with your credential documents and upload it to any employer site that tracks competencies. Some insurance firms and event organisers request proof of a provide discomfort monitoring course when contracting paramedics, so having the certificate all set shortens onboarding.
More important than the paper is the confidence you remind your team. You will discover yourself utilizing fewer words and even more framework when assessing pain, grabbing the right device readily, and charting with a quality that helps the next medical professional lug the baton. That steadiness abrades. Newer employee will replicate your flow.
Final thoughts from the coalface
Pain is not a side pursuit. It shapes physiology, decision-making, and self-respect. A targeted unit like PUAEME008 Provide discomfort monitoring offers you the behaviors to treat it well under incomplete problems. It grounds you in secure pharmacology, hones your tracking, and constructs a dependable handover regimen. For nurses, physio therapists, initially -responders, and any person with a task of care in unforeseeable settings, the skills port neatly into daily method. Pair the system with straightforward self-audit, regular refresher courses, and an eye on your regional protocols, and you will provide steadier, kinder care when it matters.